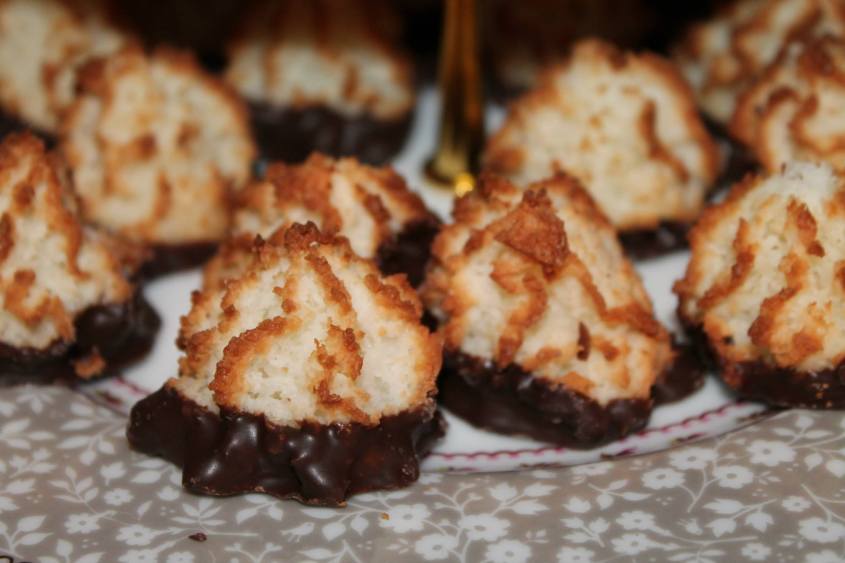Author: Steph Louka

Stephanie is an EMS Physician and Life-Member of the Virginia Beach Volunteer Rescue Squad. She lives in Richmond, VA with her husband Amir.

5 Things I Learned in Business School I Wish I’d Learned in Medical School

These days, many people enter medicine as a second career.  I am no different.  I was an undergraduate business major and worked in the corporate world of internet marketing for 6 years prior to medical school.  Perhaps a science major would have been more practical when I was spending 7 hours struggling to understand some fundamentals of molecular biology; however, my business background did occasionally give me a leg up. Going back to school at 30-something, surrounded by recent college grads, I realized a few lessons I picked up along the way weren’t necessarily obvious to others.

1. Everyone has a job, and they all matter

Despite modern movements away from it, medicine is an extremely hierarchical world.  Medical students pine for that long white coat.  Doctors bark orders at nurses without introducing themselves or asking nicely.  Phlebotomists, lab techs, housekeepers and others largely go unnoticed.
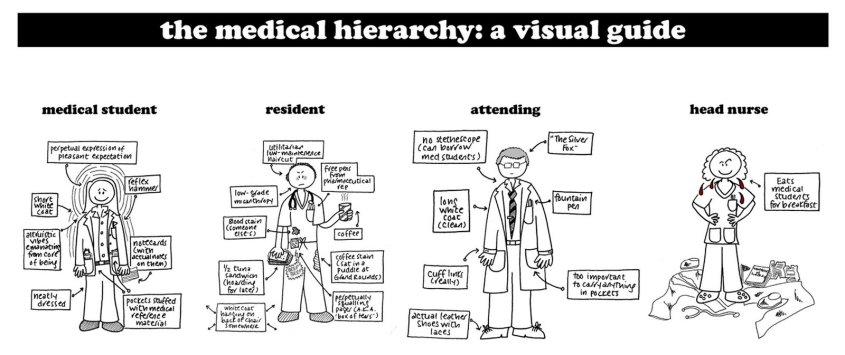
medical hierarchy
Copyright: Michelle Au | theunderweardrawer.blogspot.ca

One beautiful reality of capitalism is that jobs don’t exist unless they are vital… IMPORTANT.  In medicine, we need janitors, doctors, accountants, secretaries.  Everyone with a title has responsibilities and is therefore necessary for the organization to function.  Companies with excess overhead from superfluous staff don’t stay in business very long (VA Hospitals aside). So when the surgical consultant steals a computer terminal from the ED Tech so she can finish her note, this disrupts work flow, and sends a message that somehow the doctor’s work is more important than the ED Tech’s.  It’s just not true.  Be mindful that everyone on the team has a job to do and people will want to be on your team.

2. “For-profit = evil” is not always the case

Yes, pharmaceutical companies are responsible for their reputations as greedy, evil, for-profit companies.  Just ask Martin Shkreli.  And while it would be great to provide free medications to any and all who truly have need, research and development (R&D) of new medications is risky and costs money.  A lot of money.


On average, a new drug takes anywhere from 11-14 years to make it to market, and that’s IF the drug makes it that far.  Of any new drug developed in a lab, there is an 8% chance that drug will actually make it to market, meaning it’s prescribed by doctors for actual patients.§ The money spent on R&D for 92% of unsuccessful drugs is a true cost, and those bills still need to be paid.  Smart R&D focuses on modular development, so that one lesson learned developing a drug that failed can be applied to new research that will hopefully help a different drug get to market.

Yes there is excess and greed.  Yes Big Pharma develops drugs based on profitability, not strictly based on need.  People with “orphaned diseases” have to create non-profits and raise funds for R&D since the pharmaceutical companies won’t do it.  It’s not ideal.  Attracting the brightest minds to develop major pharmaceutical innovation requires paying people well, and I’ve yet to hear anyone tout how well-paid they are at their non-profit organization.  In the end, it’s not as simple as saying “just lower the prices or make it free.”

3. Product perception is reality

Marketing is everything.  You can have the best product in the world, but if no one knows it exists, or if consumers don’t understand what it can do for them, they won’t buy it.  Similarly, you can get all the science right in medicine, but if results, diagnoses and plans aren’t communicated, getting it right doesn’t matter.

If anything this is even more applicable in medicine than business.  While people have some innate understanding of what makes a good vacuum cleaner, they probably need more help understanding their liver failure and what treatment they need. I never assume patients understand their disease.  Taking 5 minutes to explain the relation between the liver and ascites goes a long, long way.

4. Dress & Look the Part

Being a medical professional requires knowledge, honesty and altruism.  Most people get that part right.  But professionalism in medicine also means being on time, dressing professionally, and remembering that people are always watching.  So for the EMT: put down the cigarette, tuck in your shirt and wear your gloves when needed.  For the medical student: be the first one arriving to rounds, wash your white coat (not just once a semester either), lose the stubble and open toed shoes and ditch the piercings for the day.  Doctors: wash your hands, put down your iPhone and give patients your undivided attention. All the knowledge in the world can be quickly overshadowed by a distracting or detracting exterior.

The_Doctor_Luke_Fildes
“The Doctor” by Luke Fildes

5. Listen to Customer Feedback

This is not “The customer is always right.” Medicine is different.  Just because a patient thinks he needs antibiotics for his cold doesn’t mean he should get them.  But your customers do know their bodies best and how they are feeling at the time.  If you are handing a patient discharge paperwork and they “still don’t feel right,” stop and listen.  In this case, the customer feedback is critical, and the price to pay may be high – both for the patient and for your wallet.  Any seasoned Paramedic will tell you, “When the patient says they are going to die, I believe them.”  We’ve all been there.  And if you haven’t yet, it’s just a matter of time.


So that’s it, 5 small things.  What lessons have you borrowed from an earlier career and applied to medicine?

~Steph

Screen Shot 2016-05-04 at 10.42.59 PM


§ http://www.fdareview.org/03_drug_development.php

If pages came as emojis

Right now there’s a whole new crop of medical school students graduating in a month who will start their careers as doctors on July 1. There are two things every medical student looks forward to receiving as an Intern – a long white coat and a pager. But any Resident will tell you: after your first night on call, you want to throw that pager against the wall and then stomp it into little pieces.

But what if pages, instead of boring B&W text, arrived as an emoji puzzle to decipher? That just might make getting 84 pages in a 12 hour Trauma shift slightly more tolerable.  See if you can figure out these common pages.


The “Frequent Fliers” of Pages

1.FullSizeRender_1

2.FullSizeRender_2

3.FullSizeRender_3

4.FullSizeRender_4

5.FullSizeRender_5

6.FullSizeRender_6

7.FullSizeRender_7

8.FullSizeRender_8

9.FullSizeRender_9

10.FullSizeRender_10

11.FullSizeRender_11

12.FullSizeRender

13.FullSizeRender (22)


Answers to “Frequent Fliers” Pages

  1. Mrs. Jones has a headache, please order tylenol
  2. Mr. Smith has post-op pain, please increase his pain meds
  3. Code Blue, Mr. Jones
  4. Please renew Mr. Smith’s order for restraints
  5. Mrs. Jones needs a diet order
  6. Baby Davis is febrile and has no PRNs
  7. Mr. White needs zofran for nausea
  8. Another ED admit
  9. The transfer from the OSH is on the floor
  10. Please call Pharmacy, you messed up your order again
  11. Who is going home today? -Bed Flow
  12. Mr. Smith needs a laxative
  13. Mr. Jones needs CIWA scoring

And, just for fun, some not some common but ridiculous (and true) pages:

FullSizeRender (23)

FYI: 3AM page for a “fever” of 99.0F

FullSizeRender (21)

Mr. X had a nightmare. He’s awake now.


Add your own favorite pager stories (and emoji puzzles) in the comments!

~Steph


EMS in the Hot Zone: Not so Fast

Yesterday I attended the 17th Annual Rao R. Ivatury Trauma Symposium hosted by VCU Health. I took away multiple “nuggets” to incorporate into both my prehospital and ED practice. The conference is geared towards anyone taking care of trauma patients – not just doctors but nurses, social workers, nutritionists, therapists and EMS providers, too. I highly recommend checking it out next year. Save the date: Wednesday, March 29, 2017.

Always a leader in EMS advancement, members of the Richmond Ambulance Authority (RAA) presented a poster on delivering “Good Medicine in Bad Places.” To the credit of RAA, they have developed a council with their partners in Police and Fire, to address regional response needs to unique and dangerous situations (i.e. active shooters, bombers, terrorist attacks). The data they presented is accurate – the number of incidents is rising, and the fatalities climbing.

Tactical Combat Casualty Care (TCCC) is specialized training that originated in the military. TCCC is currently being tested and studied in the civilian public safety setting. The TCCC conversation is an important one. Specialized training for these situations is an unfortunate necessity in the United States. A little background info on how these things are currently handled – most cities have specialized SWAT Medic teams comprised of talented, elite individuals adept at not only the delivery of prehospital medicine, but also in things like shooting, hand to hand combat and law enforcement. These providers are a special breed – in most cases considered the best of the best in their public safety organizations. I’ve been hearing the rumble and chatter over the last year, and it was again echoed by RAA yesterday. There is current shift in conversation towards training 100% of EMS providers to enter the warm and hot zones, to render care to patients while under fire.

It’s well known and proven that the current model of Fire/EMS waiting to enter scenes causes treatment delays that increase patient morbidity and mortality. In the December 2015 issue of the Journal of Emergency Medicine, Peter Pons of the Hartford Consensus commented that “fire/rescue and EMS personnel must work with law enforcement agencies to enter these scenes earlier than has been traditionally performed, intervene promptly to stop ongoing external hemorrhage, and incorporate basic concepts of tactical combat casualty care/tactical emergency casualty care into their education, training, and practice.” I don’t disagree with that, but I’m not sure it makes sense for us to immediately assume ALL Fire and EMS personnel should be entering scenes with active shooters – as if it’s simply one more bullet point we can just tack onto the job description.

If you think about our existing public safety system, some firefighters enjoy both patient care and fighting fire, while others if given the choice, would only ever fight fire. Similarly, some Fire and EMS providers might be part cop/soldier at heart – both capable and interested in taking on TCCC. I can assure you that not everyone on an ambulance has that police/soldier side that wants to run into an active shooter scene. Yes, EMS is a dangerous job; I’ve been punched and had a knife drawn on me in the back of the ambulance (no one tell my Mom please). Of course you can never predict what may happen and need to be ready for anything. That’s not what I am talking about in this instance. What I’m saying is that if a call goes out for an active shooter, it might not be wise to require 100% of the Fire and EMS personnel to be able to enter that active scene. Here are just a few reasons I think that could be a bad idea.

Screen Shot 2016-03-24 at 9.47.55 PM.png
Figure 1: Crossover of skills/interests in various professional fields

Negative Effects on Recruitment

As I mentioned, not all EMS providers want to take on the police/military type role of being armed with a weapon, entering dangerous scenes and providing care under fire. I don’t know how big of a chunk of people that is, as it hasn’t been surveyed yet to my knowledge. I can say personally, having been in a building with an active shooter, I have zero interest in doing so again, even with the most state of the art training. How many of the 840,000 certified EMS in the US might we lose if that bullet point gets added to the job description? Additionally, 22% of those 840,000 certified EMS personnel are volunteers. Some volunteers might want to play a part in TCCC, but if you have a family and derive no paycheck or medical benefits from your volunteer EMS gig, can you really afford to enter that scene? And what will become of all the career providers who want to do patient care, but don’t want to risk their lives. Perhaps we will we see them shift into the hospital in ED Tech, CNA and RN roles.

Distraction Away from the Medicine

Even right now, EMS education has two large components: 1) the medicine, taking vital signs, deciding what drugs to give and when and 2) operational aspects, entering a scene safely, driving an emergency vehicle, operating a portable radio, etc. As an ED Physician, I admit my bias towards the importance of #1. We’ve all had the trainee who wants to drive lights and sirens before he’s mastered taking a blood pressure. With only ~160 hours of instruction in the current NREMT course, I worry that adding the required training for TCCC will shift focus away from the medicine and negatively impact patient care, potentially leading to more morbidity and mortality across all patients, improving outcomes for those victims requiring TCCC, but leading to a net decline in overall care. Perhaps the solution will be increasing the course length. I’m not saying it can’t be done; I just hope someone studies and considers that before implementing blanket curriculum changes.

Are EMS Providers Physically Fit Enough?

Sadly, three quarters of active emergency responders in the US are overweight or obese, and 75% have been diagnosed as hypertensive or prehypertensive. All in all, we are not a healthy bunch when compared to our counterparts in Police, Fire and the military. How many EMS providers will meet the physical demands required for TCCC? Even if people want to take part in TCCC, will they meet the physical requirements to do it safely, or perhaps be pushed out of a job they love, despite providing excellent medical care.

measuringobesemanwaist0115_710826

Would it actually improve care?

To justify the risk associated with TCCC, you must be able to prove that more lives would be saved than lost, and not just during active TCCC situations, but across prehospital care as a whole. It just hasn’t been studied yet. Perhaps once studied, it will prove to be net beneficial, but right now we just don’t know.


So those are my thoughts; I’m curious to hear yours.

~Steph


Simple Steps for Throwing a British Themed Party

The great thing about a British theme is you can apply it to most types of parties. Whether you are throwing a baby shower, birthday, bon voyage, or simple dinner party, the theme is flexible and can be expressed in a number of creative ways.  My husband is 1/2 English, so we decided to throw a England/London/British themed Valentine’s Day party and called it “Love in London.”


Food

British food has a reputation for being a little dull and boring, but your spread doesn’t have to be. There are so many amazing recipes online, it can be hard to decide just what to make. We opted for sausage rolls, beef wellington (labor intensive & expensive, wouldn’t do it again), fish & chips (just buy ’em & fry ’em), cucumber & tomato salad, cucumber sandwiches and more. You can add some easy flare to your finger foods with these union jack toothpick flags.

10857217_10152816639019545_5177263491433025674_o
Simple sausage rolls with union jack flags
picrN1GjH
Marinated cucumbers, onions & tomatoes add a flavorful vegetable dish

Last but not least, don’t forget proper condiments for your amazing food.  Buy a bottle of malt vinegar for your fish & chips, and a bottle of HP sauce, and you’ve got your bases covered.

10989188_10152816640669545_2058146840114077096_o
Don’t forget the condiments!

Drink

Ok, depending on your crowd, this might be the most important aspect of the party.  There are lots of great drink options, but a British party wouldn’t be complete without Pims cup.  There’s no exact recipe you have to stick to – I like taking whatever fruit looks fresh at the store and adding it to Sprite and/or ginger beer.  For ease, you can also mix up a whole pitcher to have ready to go, similar to a sangria.

10955659_10152816639024545_8468192218854054847_o
A spin on the traditional Pims cup

Fortunately we can thank England and Scotland for having a number of great beers.  Head to your local beer/wine outlet and find the “England” section.  We went to Total Wine.  You only need a 6-pack or so of each if you are buying a big selection.  Guests enjoy trying new beers as well as old favorites.

11004572_10152816639899545_1929646650061903269_o
Assorted British beers we found at TotalWine

If you want to try something really special, and have some time to plan ahead, take a chance on a home brew and create your own.  We made a delicious London Porter in just 4 weeks using this easy home brewing kit.  We also customized the bottle to fit our theme using these handy waterproof labels for your home printer. We sealed the caps with union jack flag stickers for a finishing touch.

FullSizeRender (13).jpg
London Porter Home Brew

Dessert

There are many creative options for desserts to fit your theme.  I’m not much for baking, so I cheated and outsourced a bit of this.  The classic English dessert is a trifle, which is simply a layered dessert, typically with pudding, sponge cake and fresh fruit.

10830671_10152816639584545_4864077206661797438_o
Strawberry trifle with fresh berries

The hallmark of English tea time, after the tea of course, is small cookies.  Any small simple butter cookies will do.  You can make these, but I opted to buy pre-made.  For a mixed display, buy a box of chocolates to add to your 3-tier cake stand, and you’re ready for tea time.

Image-1 (2).jpg
Traditional 3-tier cake stands with tea time floral designs
10959946_10152816640349545_4882059641562395974_o
Store-bought coconut macaroons on the bottom tier
10952254_10152816639844545_1954935726485687109_o
Add a frilly tablecloth to complete the authentic tea time look

For another dessert option (which is a great go-to for any party or theme), consider some custom decorated cookies.  These sugar cookie masterpieces are from Cookies by Design in Virginia Beach.  They are also a hit if you have little kids attending your party.

10955559_10152816639654545_1023372447780369438_o
Hand-painted London themed cookies by Cookies by Design

Decorations

The easiest way to convey “British” visually is with the union jack flag.  You don’t have to be an artist to create cool and creative decorations.  Add a $5 union jack flag over a white tablecloth to create a bold canvas for your delicious food.

10991605_10152816639809545_4217470938099202274_o.jpg
$5 union jack flag adds an easy visual punch

Simple things like adding a sticker to your cups or nametags can help carry your theme forward in an easy way.

FullSizeRender (14)
Cute and easy cups thanks to $3.25 union jack stickers

Another option that requires no artistry, is to apply this $4 union jack duct tape to simple objects.  For this project, buy 3D cardboard letters to spell whatever you choose.  Then wrap them in the duct tape and viola!

1960944_10152816640299545_3485793302657075784_o
“LOVE” decoration made with 3D letters and duct tape for just $8

If you do consider yourself artistic or crafty, and don’t mind putting in some time cutting objects out, consider making your own garland.  Find any image you like online, print it on photo paper, cut it out, hole punch it and string them together.  Add a lace paper doily for an extra English touch.

10828142_10152816639034545_1969980728237025322_o
“Love in London” hearts strung together with lace doilies and twine
10688200_10152816640599545_7037025294879186659_o.jpg
Itty bitty hearts strung together with silver thread to make a precious garland
AN-A354
Template for tea time heart garland
10982911_10152816639424545_7327412808030885476_o
Search your house for any knick knacks that fit your theme and display them together
10928910_10152816639199545_906251322152027273_o
Colorful tissue poofs are cheap and high impact

Music

Pandora has an array of great themed channels.  The best fit for an all-ages England themed party is British Invasion Radio.

Screen Shot 2016-03-05 at 1.15.21 PM

Games & Fun

Party games and activities are tricky.  Everyone’s been to a party where games feel forced and grueling, but you don’t want a party with everyone just standing around.  Two simple activities I love are photobooths and trivia.  They are great because guests can participate on their own time throughout the party, and they don’t take any bandwidth away from the host or hostess.

Photobooth

Grab some simple props (hats, glasses, boas) and if you want to go big, a life-size celebrity cut-out.  Kate Middleton and Queenie were the life of the party.

12744351_10153573123849545_4344595375962939833_n

If you entertain a lot, consider investing in the modern polaroid, the FujiFilm Instax mini camera.  It instantly prints a polaroid-style photo that makes a great takeaway memory for your guests.

Trivia

Create a set of questions related to your theme and post them, along with pens and ballots, for guests to fill out.  Winner gets a prize!

12734057_10153573123949545_1033623859226666660_n.jpg

So that’s it, ideas for food, drinks, music, decorations and activities for your next London/British/English themed party.  For additional ideas not mentioned here, check out the Love in London Pinterest board.

~Steph

12734068_10153573123929545_4336717189662421359_n

A Neuroscientist’s Look Back on his July 4th Ambulance Ride-Along

On July 4, 2013, Dr. Paul Aravich joined TeamLouka on the ambulance as an observer.  He was asked to jot down a few thoughts on his experience.  His essay is shared below.

~Steph


Reflections of a Virginia Beach Volunteer Rescue Squad Lay Observer, July 4, 2013. 

Paul F. Aravich, PhD
998839_10151588264079545_313081585_nStephanie Krebs and Amir Louka are two VBVRS volunteers and EVMS medical students who are “social change agents and leaders for the greater good of the community.” They invited me to run with them at Station 8 on Independence Day, 2013. I saw 2 other EVMS students that day who I also admire: an exceptional paramedic who is a new medical student, and a Navy veteran and physician assistant student who is as gentle as he is tall. I witnessed great respect between VBVRS, fire department and ED personnel in almost every instance. And I saw cutting-edge wireless technology and state-of-the-art equipment—although I am still not sure if it the ambulance is a box or a truck.

At the station I hung-out with a volunteer from York County who served at the World Trade Centers and Katrina, a new EVMS graduate student, a senior volunteer who is a builder of persons as well as of homes and barbecues, a critical care nurse from Chesapeake, and an accountant. We talked about abandoned older persons, defensive medicine, how to read an ECG, challenging behaviors, not getting T-boned at intersections, altruism, family, political turmoil in Egypt, and who catches a baseball better, the bulked-up waiter at IHOP or a nerd like me who, like Winnie the Pooh, is actually a “bear of little brain.” We also wondered if we heard the dispatcher correctly that a person got stabbed in the cheek with a fork. At one point Stephanie bravely gave me her humerus (which is pretty funny) and Amir gave me his stethoscope and cuff so I could learn the proper way to take a blood pressure. Thankfully, Stephanie’s paresthesia lasted only a few minutes. At the nearby Oceania Fire Station we laughed with an Army veteran who has seen more than his fair share of tragedies, discussed the merits of Cheryl Crow as a History Channel commentator, and had a surprising conversation about the nutritional problems of hot dogs that made me worry that firefighters may someday eschew donuts. I saw camaraderie being built during the down times as well as during the calls. And, I talked with a squad member and former court official about the ones that were saved, the ones that got away, and an aging parent with dementia. I was reminded that all of us have to hold on to our victories, let go of our defeats, and understand that we’re in this together.

1040465_591569347561093_149799321_o
Dr. Aravich & us outside Sentara Virginia Beach General Hospital

Throughout the day I was humbled and inspired by consistent displays of commitment and professionalism, humanism and compassion, and collegiality and mutual support. I saw a successfully aged person with a rare and serious injury that causes significant pain in others but did not in her and wondered if it would steal her independence. I saw an isolated older woman and cancer survivor with depression and abdominal pain and hoped that her GI cancer was not coming back. I saw a frightened young mother fighting addiction and hoped that today will be the first day of the rest of her life. I saw an injured skateboarder who should have known about helmets. I saw a scared older person with breathlessness and fatigue and a family history of heart attack who should not have been cutting grass in the middle of a hot day. I saw the basic life support team immediately recognized the severity of this situation and calmly and effectively take precautions before the paramedic arrived. I saw the paramedic take an ECG in the truck and learned later that it showed the more severe type of heart attack called a STEMI (ST Elevation Myocardial Infarction). I saw the paramedic taking care of this person inside the moving and turning ambulance by, e.g., drawing blood, giving nitroglycerine, sending ECG telemetry to the ED, and offering words of encouragement. Finally, on the 4th of July I saw a crying spouse, caring neighbors, and engaged citizens volunteering to help others when almost everyone else was relaxing.

If, in the Jeffersonian tradition, the pursuit of happiness importantly involves pursuing the greater good, then the VBVRS is full of happy people. And, if people are not distinguished by doing what they have to do but are distinguished by doing what they don’t have to do, the VBVRS is full of very distinguished people. Thank you Stephanie, Amir and the VBVRS for allowing me to see the important volunteer work you do without charging patients. Lives do indeed need saving, both physically and emotionally. All of you saved lives today. Is there any greater compliment? Meantime, a few words about hot dogs: it is OK to bad-mouth hotdogs—but not on the 4th of July.


Dr. Paul Aravich is a behavioral neuroscientist and Professor of Pathology & Anatomy, Internal Medicine, and Physical Medicine and Rehabilitation at Eastern Virginia Medical School (EVMS). He is the former of the Virginia Brain Injury Council and its Ad Hoc Neurobehavioral Committee. He also chaired the Virginia Governor’s Public Guardian & Conservator Advisory Board and sits on the Boards of the Mary Buckley Foundation for brain injury survivors & their families; the I Need a Lighthouse Foundation for suicide awareness; and Alternatives, a nationally recognized youth empowerment organization. He won an AOA Glaser Distinguished Teacher Award. It is the highest award for medical education in the United States and Canada and is presented at the annual meeting of the Association of American Medical Colleges. He also won a Virginia State Council of Higher Education Outstanding Faculty Award, which is Virginia’s highest award for research, teaching and service.
10273447_10152226339749545_1587305735930057894_n
EVMS Graduation, May 2014
You can view his 2009 TEDTalk here:
To learn more about volunteer opportunities with the Virginia Beach Rescue Squads, visit LivesNeedSaving.com.