Category: Emergency Medicine

5 Things I Learned in Business School I Wish I’d Learned in Medical School

These days, many people enter medicine as a second career.  I am no different.  I was an undergraduate business major and worked in the corporate world of internet marketing for 6 years prior to medical school.  Perhaps a science major would have been more practical when I was spending 7 hours struggling to understand some fundamentals of molecular biology; however, my business background did occasionally give me a leg up. Going back to school at 30-something, surrounded by recent college grads, I realized a few lessons I picked up along the way weren’t necessarily obvious to others.

1. Everyone has a job, and they all matter

Despite modern movements away from it, medicine is an extremely hierarchical world.  Medical students pine for that long white coat.  Doctors bark orders at nurses without introducing themselves or asking nicely.  Phlebotomists, lab techs, housekeepers and others largely go unnoticed.
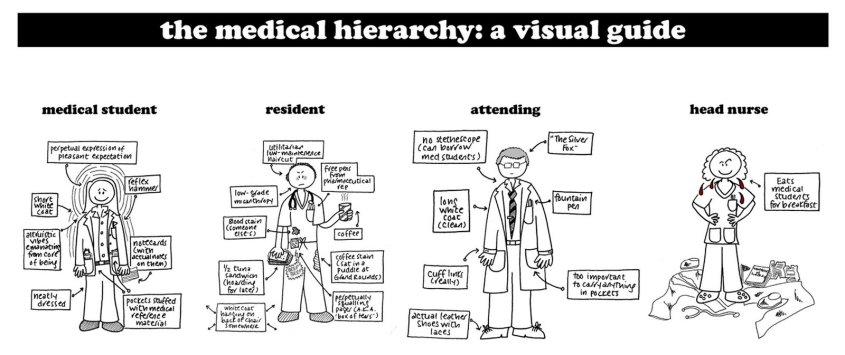
medical hierarchy
Copyright: Michelle Au | theunderweardrawer.blogspot.ca

One beautiful reality of capitalism is that jobs don’t exist unless they are vital… IMPORTANT.  In medicine, we need janitors, doctors, accountants, secretaries.  Everyone with a title has responsibilities and is therefore necessary for the organization to function.  Companies with excess overhead from superfluous staff don’t stay in business very long (VA Hospitals aside). So when the surgical consultant steals a computer terminal from the ED Tech so she can finish her note, this disrupts work flow, and sends a message that somehow the doctor’s work is more important than the ED Tech’s.  It’s just not true.  Be mindful that everyone on the team has a job to do and people will want to be on your team.

2. “For-profit = evil” is not always the case

Yes, pharmaceutical companies are responsible for their reputations as greedy, evil, for-profit companies.  Just ask Martin Shkreli.  And while it would be great to provide free medications to any and all who truly have need, research and development (R&D) of new medications is risky and costs money.  A lot of money.


On average, a new drug takes anywhere from 11-14 years to make it to market, and that’s IF the drug makes it that far.  Of any new drug developed in a lab, there is an 8% chance that drug will actually make it to market, meaning it’s prescribed by doctors for actual patients.§ The money spent on R&D for 92% of unsuccessful drugs is a true cost, and those bills still need to be paid.  Smart R&D focuses on modular development, so that one lesson learned developing a drug that failed can be applied to new research that will hopefully help a different drug get to market.

Yes there is excess and greed.  Yes Big Pharma develops drugs based on profitability, not strictly based on need.  People with “orphaned diseases” have to create non-profits and raise funds for R&D since the pharmaceutical companies won’t do it.  It’s not ideal.  Attracting the brightest minds to develop major pharmaceutical innovation requires paying people well, and I’ve yet to hear anyone tout how well-paid they are at their non-profit organization.  In the end, it’s not as simple as saying “just lower the prices or make it free.”

3. Product perception is reality

Marketing is everything.  You can have the best product in the world, but if no one knows it exists, or if consumers don’t understand what it can do for them, they won’t buy it.  Similarly, you can get all the science right in medicine, but if results, diagnoses and plans aren’t communicated, getting it right doesn’t matter.

If anything this is even more applicable in medicine than business.  While people have some innate understanding of what makes a good vacuum cleaner, they probably need more help understanding their liver failure and what treatment they need. I never assume patients understand their disease.  Taking 5 minutes to explain the relation between the liver and ascites goes a long, long way.

4. Dress & Look the Part

Being a medical professional requires knowledge, honesty and altruism.  Most people get that part right.  But professionalism in medicine also means being on time, dressing professionally, and remembering that people are always watching.  So for the EMT: put down the cigarette, tuck in your shirt and wear your gloves when needed.  For the medical student: be the first one arriving to rounds, wash your white coat (not just once a semester either), lose the stubble and open toed shoes and ditch the piercings for the day.  Doctors: wash your hands, put down your iPhone and give patients your undivided attention. All the knowledge in the world can be quickly overshadowed by a distracting or detracting exterior.

The_Doctor_Luke_Fildes
“The Doctor” by Luke Fildes

5. Listen to Customer Feedback

This is not “The customer is always right.” Medicine is different.  Just because a patient thinks he needs antibiotics for his cold doesn’t mean he should get them.  But your customers do know their bodies best and how they are feeling at the time.  If you are handing a patient discharge paperwork and they “still don’t feel right,” stop and listen.  In this case, the customer feedback is critical, and the price to pay may be high – both for the patient and for your wallet.  Any seasoned Paramedic will tell you, “When the patient says they are going to die, I believe them.”  We’ve all been there.  And if you haven’t yet, it’s just a matter of time.


So that’s it, 5 small things.  What lessons have you borrowed from an earlier career and applied to medicine?

~Steph

Screen Shot 2016-05-04 at 10.42.59 PM


§ http://www.fdareview.org/03_drug_development.php

Celebrate the Small Stuff: Surviving the Marathon of Medical Training

In just two short months, thousands of newly minted young physicians will be walking into new hospitals, new jobs, and new responsibility. They’ll notice something unfamiliar tickling their calves on that first day – a long white coat having replaced the short one, which in our case went up in flames just days earlier. They’ll be excited and terrified, nervous and naïve.

A doctor’s “intern year” has become something of a legend in pop-culture, portrayed as twelve months of rude awakenings, sleep deprivation and verbal abuse, +/- a love triangle or two. Having been there, done that and proudly owning the t-shirt, I can say the reality couldn’t be further from the truth – at least it doesn’t have to be.*

To all the newbies out there – yes, there will be long hours and sleepless nights. You’ll occasionally go a full week without seeing your loved ones and eat whatever/whenever you can. Med school will seem a lifetime ago when you’re being asked at 3am what to do for a dying person, and you’ll wonder why they never taught you all the things that matter. But Steph and I have stumbled across the solution to all of that.

10258258_10152226340584545_6611748125605401302_o (1)
Champagne celebration for med school graduation | Photo credit: Amy McClure

We celebrate the small stuff.

Sure we popped champagne like we’d just won a Grand Prix on graduation day, but we’ve also raised a glass to finishing tough rotations, making a clutch diagnosis and running our first double cardiac arrest. We’ve made a ritual of rare Sunday mornings off together with a supply of cinnamon buns always available, just in case. Sometimes we just celebrate because it’s Tuesday and we can. By making a big deal of small victories, the roadblocks become surmountable.

https://www.instagram.com/p/BE2LZoYPaII/


Don’t get me wrong – residency is tough. In the past month, three of my patients have died, and I’ve told four others they have cancer. But for every bad day I have had there have been a dozen that left me thinking, “I have the best job in the world.”

I encourage all the newbies out there to approach this next chapter the same way. And remember: when the champagne runs out, there’s always more coffee.

https://www.instagram.com/p/91JrKjPaPL/


*Note: does not apply to general surgery residents. Your life will suck.


How do you like to celebrate the small stuff?

~Amir


https://www.instagram.com/p/6lCjdKlzlj/

If pages came as emojis

Right now there’s a whole new crop of medical school students graduating in a month who will start their careers as doctors on July 1. There are two things every medical student looks forward to receiving as an Intern – a long white coat and a pager. But any Resident will tell you: after your first night on call, you want to throw that pager against the wall and then stomp it into little pieces.

But what if pages, instead of boring B&W text, arrived as an emoji puzzle to decipher? That just might make getting 84 pages in a 12 hour Trauma shift slightly more tolerable.  See if you can figure out these common pages.


The “Frequent Fliers” of Pages

1.FullSizeRender_1

2.FullSizeRender_2

3.FullSizeRender_3

4.FullSizeRender_4

5.FullSizeRender_5

6.FullSizeRender_6

7.FullSizeRender_7

8.FullSizeRender_8

9.FullSizeRender_9

10.FullSizeRender_10

11.FullSizeRender_11

12.FullSizeRender

13.FullSizeRender (22)


Answers to “Frequent Fliers” Pages

  1. Mrs. Jones has a headache, please order tylenol
  2. Mr. Smith has post-op pain, please increase his pain meds
  3. Code Blue, Mr. Jones
  4. Please renew Mr. Smith’s order for restraints
  5. Mrs. Jones needs a diet order
  6. Baby Davis is febrile and has no PRNs
  7. Mr. White needs zofran for nausea
  8. Another ED admit
  9. The transfer from the OSH is on the floor
  10. Please call Pharmacy, you messed up your order again
  11. Who is going home today? -Bed Flow
  12. Mr. Smith needs a laxative
  13. Mr. Jones needs CIWA scoring

And, just for fun, some not some common but ridiculous (and true) pages:

FullSizeRender (23)

FYI: 3AM page for a “fever” of 99.0F

FullSizeRender (21)

Mr. X had a nightmare. He’s awake now.


Add your own favorite pager stories (and emoji puzzles) in the comments!

~Steph


EMS in the Hot Zone: Not so Fast

Yesterday I attended the 17th Annual Rao R. Ivatury Trauma Symposium hosted by VCU Health. I took away multiple “nuggets” to incorporate into both my prehospital and ED practice. The conference is geared towards anyone taking care of trauma patients – not just doctors but nurses, social workers, nutritionists, therapists and EMS providers, too. I highly recommend checking it out next year. Save the date: Wednesday, March 29, 2017.

Always a leader in EMS advancement, members of the Richmond Ambulance Authority (RAA) presented a poster on delivering “Good Medicine in Bad Places.” To the credit of RAA, they have developed a council with their partners in Police and Fire, to address regional response needs to unique and dangerous situations (i.e. active shooters, bombers, terrorist attacks). The data they presented is accurate – the number of incidents is rising, and the fatalities climbing.

Tactical Combat Casualty Care (TCCC) is specialized training that originated in the military. TCCC is currently being tested and studied in the civilian public safety setting. The TCCC conversation is an important one. Specialized training for these situations is an unfortunate necessity in the United States. A little background info on how these things are currently handled – most cities have specialized SWAT Medic teams comprised of talented, elite individuals adept at not only the delivery of prehospital medicine, but also in things like shooting, hand to hand combat and law enforcement. These providers are a special breed – in most cases considered the best of the best in their public safety organizations. I’ve been hearing the rumble and chatter over the last year, and it was again echoed by RAA yesterday. There is current shift in conversation towards training 100% of EMS providers to enter the warm and hot zones, to render care to patients while under fire.

It’s well known and proven that the current model of Fire/EMS waiting to enter scenes causes treatment delays that increase patient morbidity and mortality. In the December 2015 issue of the Journal of Emergency Medicine, Peter Pons of the Hartford Consensus commented that “fire/rescue and EMS personnel must work with law enforcement agencies to enter these scenes earlier than has been traditionally performed, intervene promptly to stop ongoing external hemorrhage, and incorporate basic concepts of tactical combat casualty care/tactical emergency casualty care into their education, training, and practice.” I don’t disagree with that, but I’m not sure it makes sense for us to immediately assume ALL Fire and EMS personnel should be entering scenes with active shooters – as if it’s simply one more bullet point we can just tack onto the job description.

If you think about our existing public safety system, some firefighters enjoy both patient care and fighting fire, while others if given the choice, would only ever fight fire. Similarly, some Fire and EMS providers might be part cop/soldier at heart – both capable and interested in taking on TCCC. I can assure you that not everyone on an ambulance has that police/soldier side that wants to run into an active shooter scene. Yes, EMS is a dangerous job; I’ve been punched and had a knife drawn on me in the back of the ambulance (no one tell my Mom please). Of course you can never predict what may happen and need to be ready for anything. That’s not what I am talking about in this instance. What I’m saying is that if a call goes out for an active shooter, it might not be wise to require 100% of the Fire and EMS personnel to be able to enter that active scene. Here are just a few reasons I think that could be a bad idea.

Screen Shot 2016-03-24 at 9.47.55 PM.png
Figure 1: Crossover of skills/interests in various professional fields

Negative Effects on Recruitment

As I mentioned, not all EMS providers want to take on the police/military type role of being armed with a weapon, entering dangerous scenes and providing care under fire. I don’t know how big of a chunk of people that is, as it hasn’t been surveyed yet to my knowledge. I can say personally, having been in a building with an active shooter, I have zero interest in doing so again, even with the most state of the art training. How many of the 840,000 certified EMS in the US might we lose if that bullet point gets added to the job description? Additionally, 22% of those 840,000 certified EMS personnel are volunteers. Some volunteers might want to play a part in TCCC, but if you have a family and derive no paycheck or medical benefits from your volunteer EMS gig, can you really afford to enter that scene? And what will become of all the career providers who want to do patient care, but don’t want to risk their lives. Perhaps we will we see them shift into the hospital in ED Tech, CNA and RN roles.

Distraction Away from the Medicine

Even right now, EMS education has two large components: 1) the medicine, taking vital signs, deciding what drugs to give and when and 2) operational aspects, entering a scene safely, driving an emergency vehicle, operating a portable radio, etc. As an ED Physician, I admit my bias towards the importance of #1. We’ve all had the trainee who wants to drive lights and sirens before he’s mastered taking a blood pressure. With only ~160 hours of instruction in the current NREMT course, I worry that adding the required training for TCCC will shift focus away from the medicine and negatively impact patient care, potentially leading to more morbidity and mortality across all patients, improving outcomes for those victims requiring TCCC, but leading to a net decline in overall care. Perhaps the solution will be increasing the course length. I’m not saying it can’t be done; I just hope someone studies and considers that before implementing blanket curriculum changes.

Are EMS Providers Physically Fit Enough?

Sadly, three quarters of active emergency responders in the US are overweight or obese, and 75% have been diagnosed as hypertensive or prehypertensive. All in all, we are not a healthy bunch when compared to our counterparts in Police, Fire and the military. How many EMS providers will meet the physical demands required for TCCC? Even if people want to take part in TCCC, will they meet the physical requirements to do it safely, or perhaps be pushed out of a job they love, despite providing excellent medical care.

measuringobesemanwaist0115_710826

Would it actually improve care?

To justify the risk associated with TCCC, you must be able to prove that more lives would be saved than lost, and not just during active TCCC situations, but across prehospital care as a whole. It just hasn’t been studied yet. Perhaps once studied, it will prove to be net beneficial, but right now we just don’t know.


So those are my thoughts; I’m curious to hear yours.

~Steph


Go Go Gadget Defibrillator: What I Do and Don’t Carry on Duty

Everything lies on a spectrum, especially in the world of medicine, and a medic’s choice of personal kit is no different. From Mr. “I don’t care if it’s a rectal bleed, gloves are for rookies,” to your favorite Rescue Rambo, who would use a Medivac unit as his daily commuter if he could, we each choose a few (possibly) useful things to keep within arm’s reach while on duty. While Steph and I may work at the busiest Level 1 in the state, and have any and all imaginable technology at our disposal while there, being outside the hospital is a different story entirely. So here’s a look at what I choose to bring along and what I feel can make a difference when the tones go off.

ambulance rookie
Photo copyright: The Lonely Medic

1. My very own pulse ox

A few years ago these things could set you back a few hundred dollars, but now you can pick one up on Amazon for about $20 with free shipping. Beyond the general appearance of a patient (Again, a spectrum: from “Ugh, why 3am?” to “Oh… that can’t be good.”) few things can give you as much information about the person in front of you as this tiny device. Patient looks like he’s working to breath? Maybe it has something to do with that O2 sat of 65% – better call back the engine you just cancelled.

It’s part of my approach to almost every patient I encounter – I introduce myself while lowering myself to their level (standing over a patient is imposing and dominant, even if you’re not 6’5” like me, and not generally comforting to little old ladies). I slip on a pulse ox while taking his/her hand and wrist to feel a pulse. As well as instantly assessing perfusion, motor and sensory function, that simple, brief human contact goes a long way in gaining trust and establishing rapport. Fun fact: the servers at Hooters do exactly the same thing.

2. A radio

We take them for granted, but this thing is your ticket to unlimited resources on-scene and your lifeline when SHTF (like this day in Virginia Beach in April 2012). Need manpower? Engine’s en route. Leave something in the truck? Someone can grab it on the way in. When my partner had a seizure on duty and wasn’t breathing, I hit that little orange button and said a few words… You’d have thought WWIII had broken out. When every unit in a five mile radius was headed my way in seconds, I realized that motorola is more than a faceless voice that tells you where to go. I keep mine in a reflective shoulder strap for added safety, to which I also attach the pulse ox for quick and easy access.

dont_push_button

3. A knife/multitool/trauma shears

I carry one of the above, depending which I can find while getting ready for duty at 4am. I don’t carry all of them. I don’t carry multiples of any of them. No boot knives or ninja stars, no Ka-Bar combat bayonets. It’s volunteer EMS, not Vietnam. I use it to cut stuff.

image (2) RAMBO
Every squad has this dude.  You know who I’m talking about.

4. A mini maglite

One of the things I love about getting outside the hospital are the places we go. We often see another side of society we otherwise never would – dark alleys, abandoned buildings, and deep ditches in the dead of night. I’ve had a mini maglite since day one, and it’s never let me down. If I have a funny feeling about a place, I might bring along one of the big D cells we keep in the truck, but 99% of the time the mini gets the job done.

5. Steel toed boots and well made pants 

Steph regularly wears shorts and sneakers on duty. I just don’t get it. Even if it’s 100F in the shade, you’ll find me sweating in my 5.11s. Who knows where you’ll find yourself, or what you’ll find yourself in, on the next call. Safety first.

image (3)

6. My brain 

Forget everything I’ve said up to this point. Brainpower is the only thing you NEED to bring along. This is how you’ll navigate tough problems, assess complex patients and choose the right interventions. Without it, you’re no good to anyone. With it, you’re a real-life hero. Signing up to take care of people in need is also a commitment to lifelong learning. You owe it to your patients to practice, stay up to date, to learn new things and continually improve. If you’re reading this, you’re probably on the right track. And keep in mind, your partner probably has one too, complete with its own experience, training and know-how. Use ‘em.

image (1) HOUSE

Honorable Mention: A stethoscope 

You might have noticed the most ubiquitous piece of medical equipment missing from the list above. Truth be told, these things are living dinosaurs. This year happens to be the 200th anniversary of the stethoscope’s invention, but contrary to what Mr. Littman would have you believe, they have barely changed in all that time. Too often, the scene is just too noisy and chaotic get an accurate exam, and in most circumstances requiring immediate intervention you can get the same information in other ways. Breathing difficulty with a history of both CHF and COPD? Try a neb while looking for other signs like JVD and pitting edema. It’s rarely exclusively one or the other. Tube placement? If you’re not using end-tidal you’re behind the times. Trauma and hypotension? Prepare to dart the chest and get moving.

3 dishes
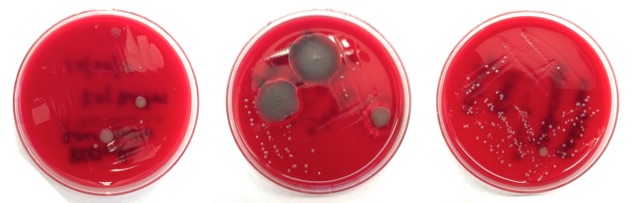
For the record, using the shared stethoscope in the jump bag is not an option. This is what grew from swabs Steph took off a stethoscope.

In my experience, the rubber necklace acts more like a police officers badge or firefighter’s helmet than a diagnostic instrument in the field, clearly identifying you as medical personnel. That’s a perfectly good reason to keep one with you though, so feel free. But if you’re like me, it usually stays in the truck.

All that said, the day they come out with a pocket defibrillator, I’ll be first in line.

~Amir

 336111_10151109792184545_1500950861_o (1)